





















Aborto de Repetición y Laparoscopia
“A full-term pregnancy with severe uterine factor infertility and recurrent pregnancy loss (13 miscarriages): Complex laparoscopic myomectomy, high abdominal cerclage”

1. Extract
- Patient Profile: International patient referred from the United Kingdom with a history of extreme reproductive complexity: 13 pregnancy losses (7 of which were late second-trimester losses due to severe cervical incompetence).
- Diagnostic Findings: Macroscopically polymyomatous uterus with severe cavitary deformation, diffuse adenomyosis, enlargement of the uterus extending to the umbilical region, and a previous abdominal cerclage in a distal/suboptimal position.
- Surgical and Medical Approach:
-
- OBTAINING a euploid embryo via IVF–ICSI with PGT-A using the patient’s own oocytes.
- Multiple laparoscopic myomectomy (removal of 6–7 myomas whilst preserving the endometrium).
- REMOVAL and repositioning of laparoscopic abdominal cerclage via the high (isthmo-cervical) approach.
- Hysteroscopy for review and endometrial regenerative treatment with PRP.
- Obstetric Outcome: Birth of a healthy live female infant at 34 weeks’ gestation via planned caesarean section in June 2026.
2. Clinical History and Reproductive Anamnesis
Patient with a reproductive history of high obstetric complexity characterised by repeated spontaneous pregnancies without a live-born infant.
History of Pregnancy Losses:
- 13 pregnancy losses in total:
- 6 miscarriages in the first trimester.
- 7 late pregnancy losses (weeks 16 to 22) secondary to severe isthmocervical insufficiency.
- Assisted Reproductive Treatments: 2 biochemical pregnancies following previous cycles.
- Previous Interventions: Abdominal cerclage via laparotomy/laparoscopy performed in 2019 in her country of origin, which failed to prevent subsequent pregnancy losses.
3. Anatomical Diagnosis of the Uterus
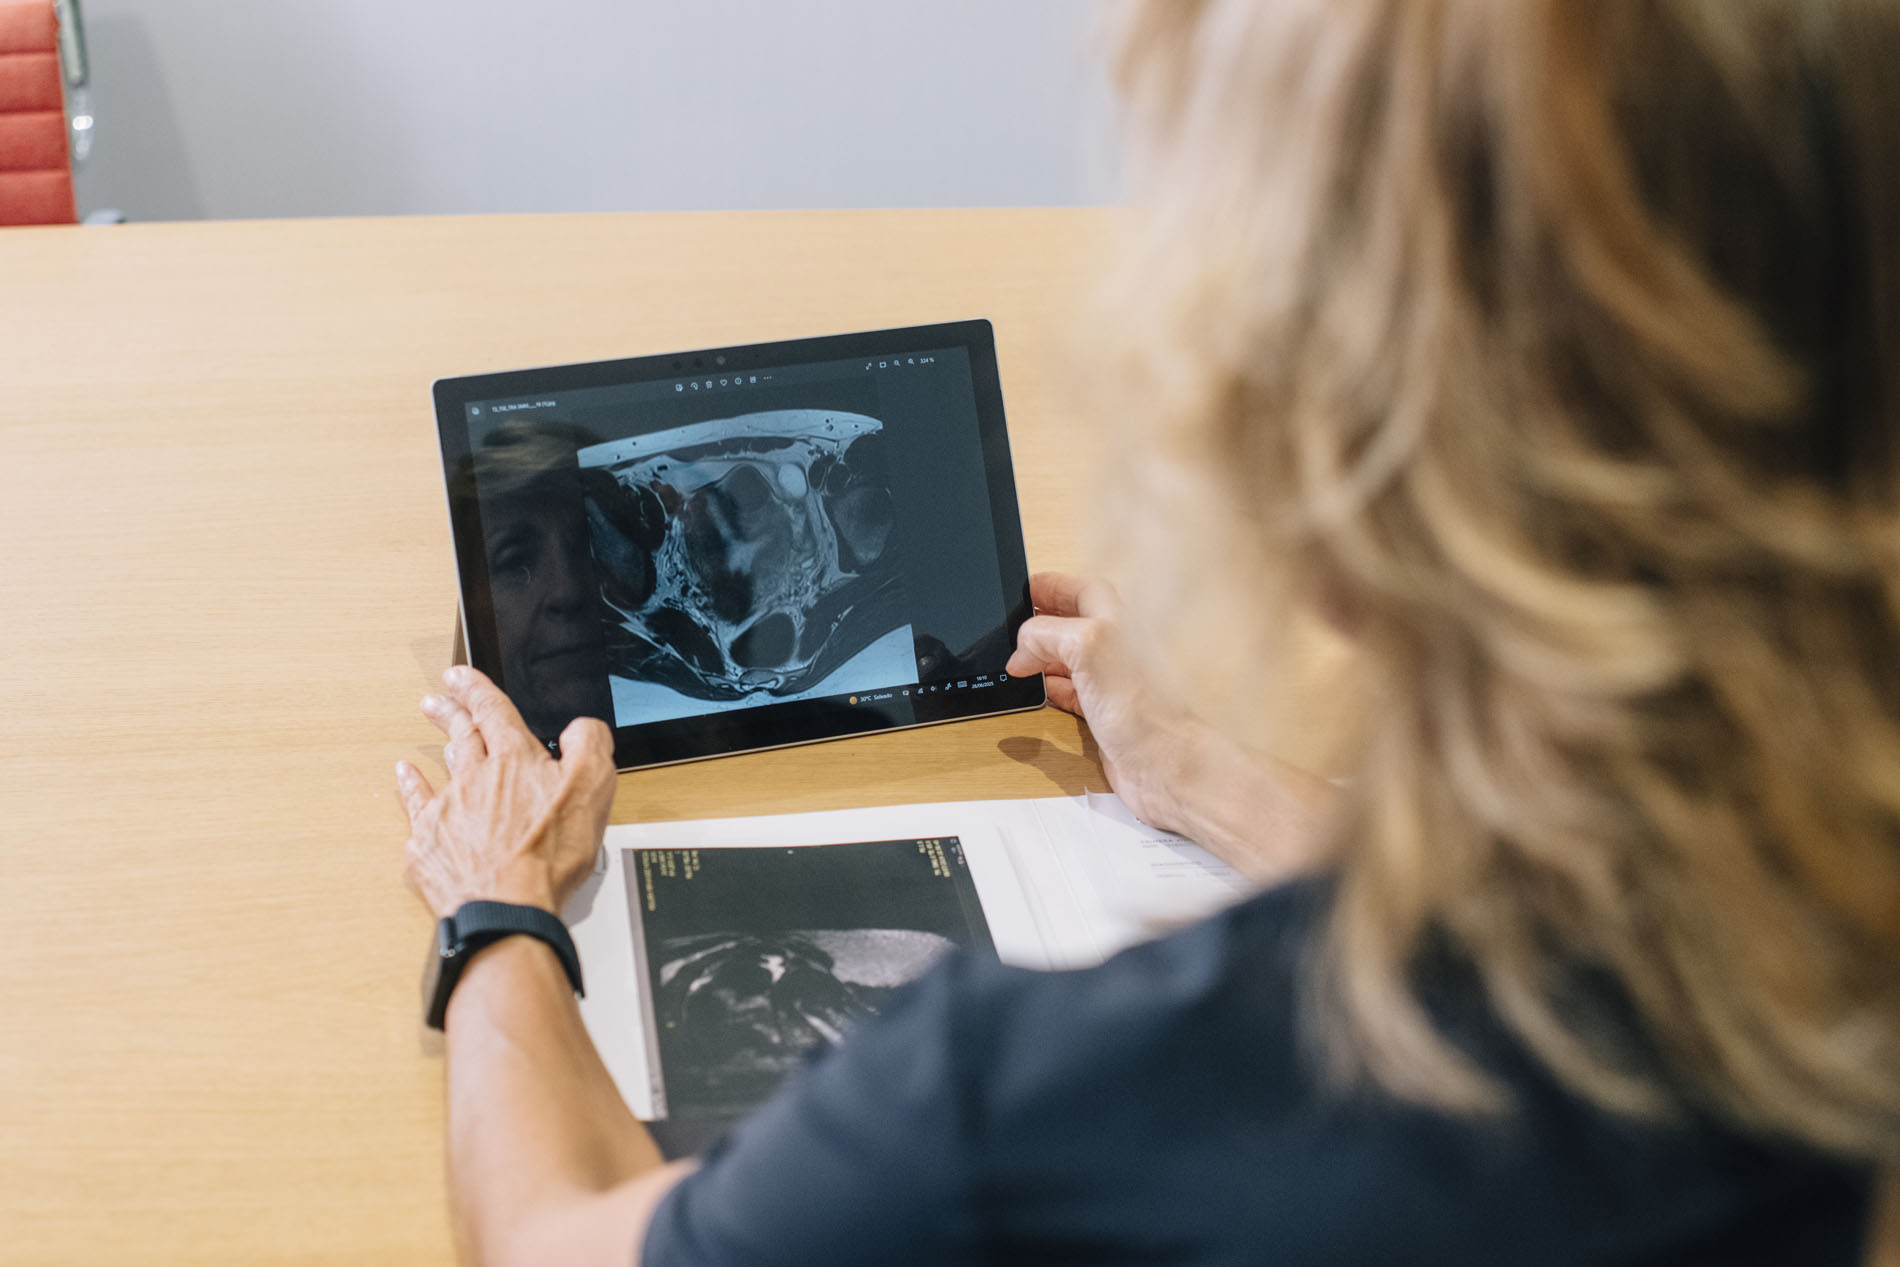
On admission to our clinic, a comprehensive morphological assessment was carried out using three-dimensional (3D) ultrasound with hysterosonography and pelvic magnetic resonance imaging.
Initial uterine diagnosis
- Polymyomatous uterus (umbilical volume)
- Adenomyosis of the posterior uterine wall
- Severe deformation of the uterine cavity
- Previously performed, poorly positioned abdominal cerclage
4. Main Findings
- Polymyomatous uterus and uterine adenomyosis: Severely enlarged uterus (equivalent to a gestational age of 18–20 weeks, extending to the umbilical scar), with multiple leiomyomas of intramural and subendometrial distribution, associated with extensive posterior adenomyosis.
- Cavity Deformation: Intrinsic compression and distortion of the endometrial cavity, preventing proper implantation and placental growth.
- Failure of Previous Cerclage: The previous cerclage band was positioned too low (distally), rendering it ineffective in the face of the patient’s mechanofunctional cervical incompetence.
- Step-by-Step Treatment Strategy
Due to the extremely high risk of uterine rupture and implantation failure, a four-phase sequential protocol was designed:
Phase 1: Embryo Genetic Testing and Obtaining a Euploid Embryo (October 2024)
Before subjecting the patient to major invasive surgery, it was essential to ensure the genetic viability of the embryo.
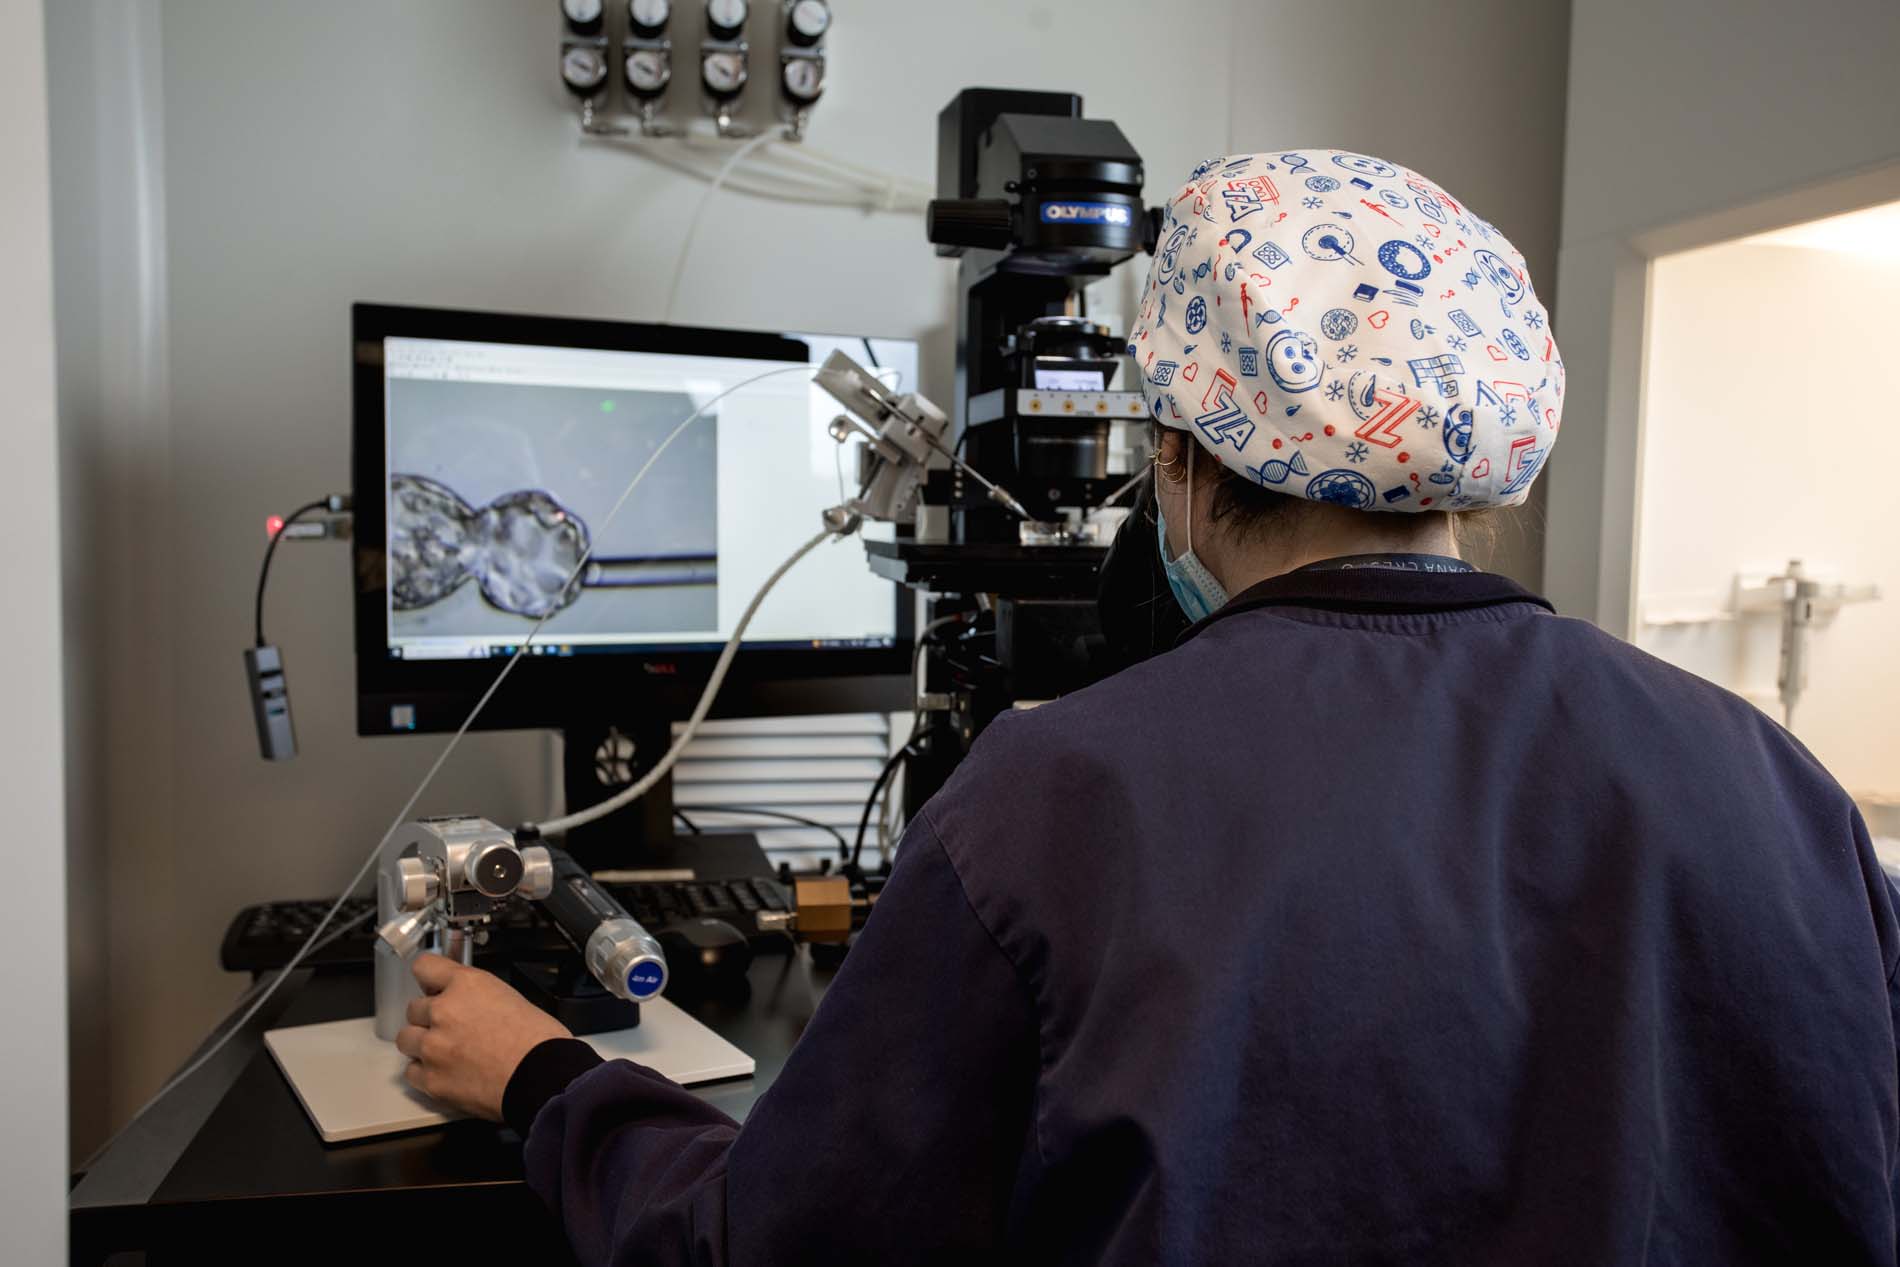
- Ovarian Stimulation: 16 mature oocytes were retrieved.
- IVF + PGT-A: A single euploid (chromosomally healthy) embryo was obtained. The entire subsequent strategy was designed to maximise the chances of success with this single embryo.
Phase 2: Surgical Reconstruction of the Uterine Wall and Recerclage (March 2025)
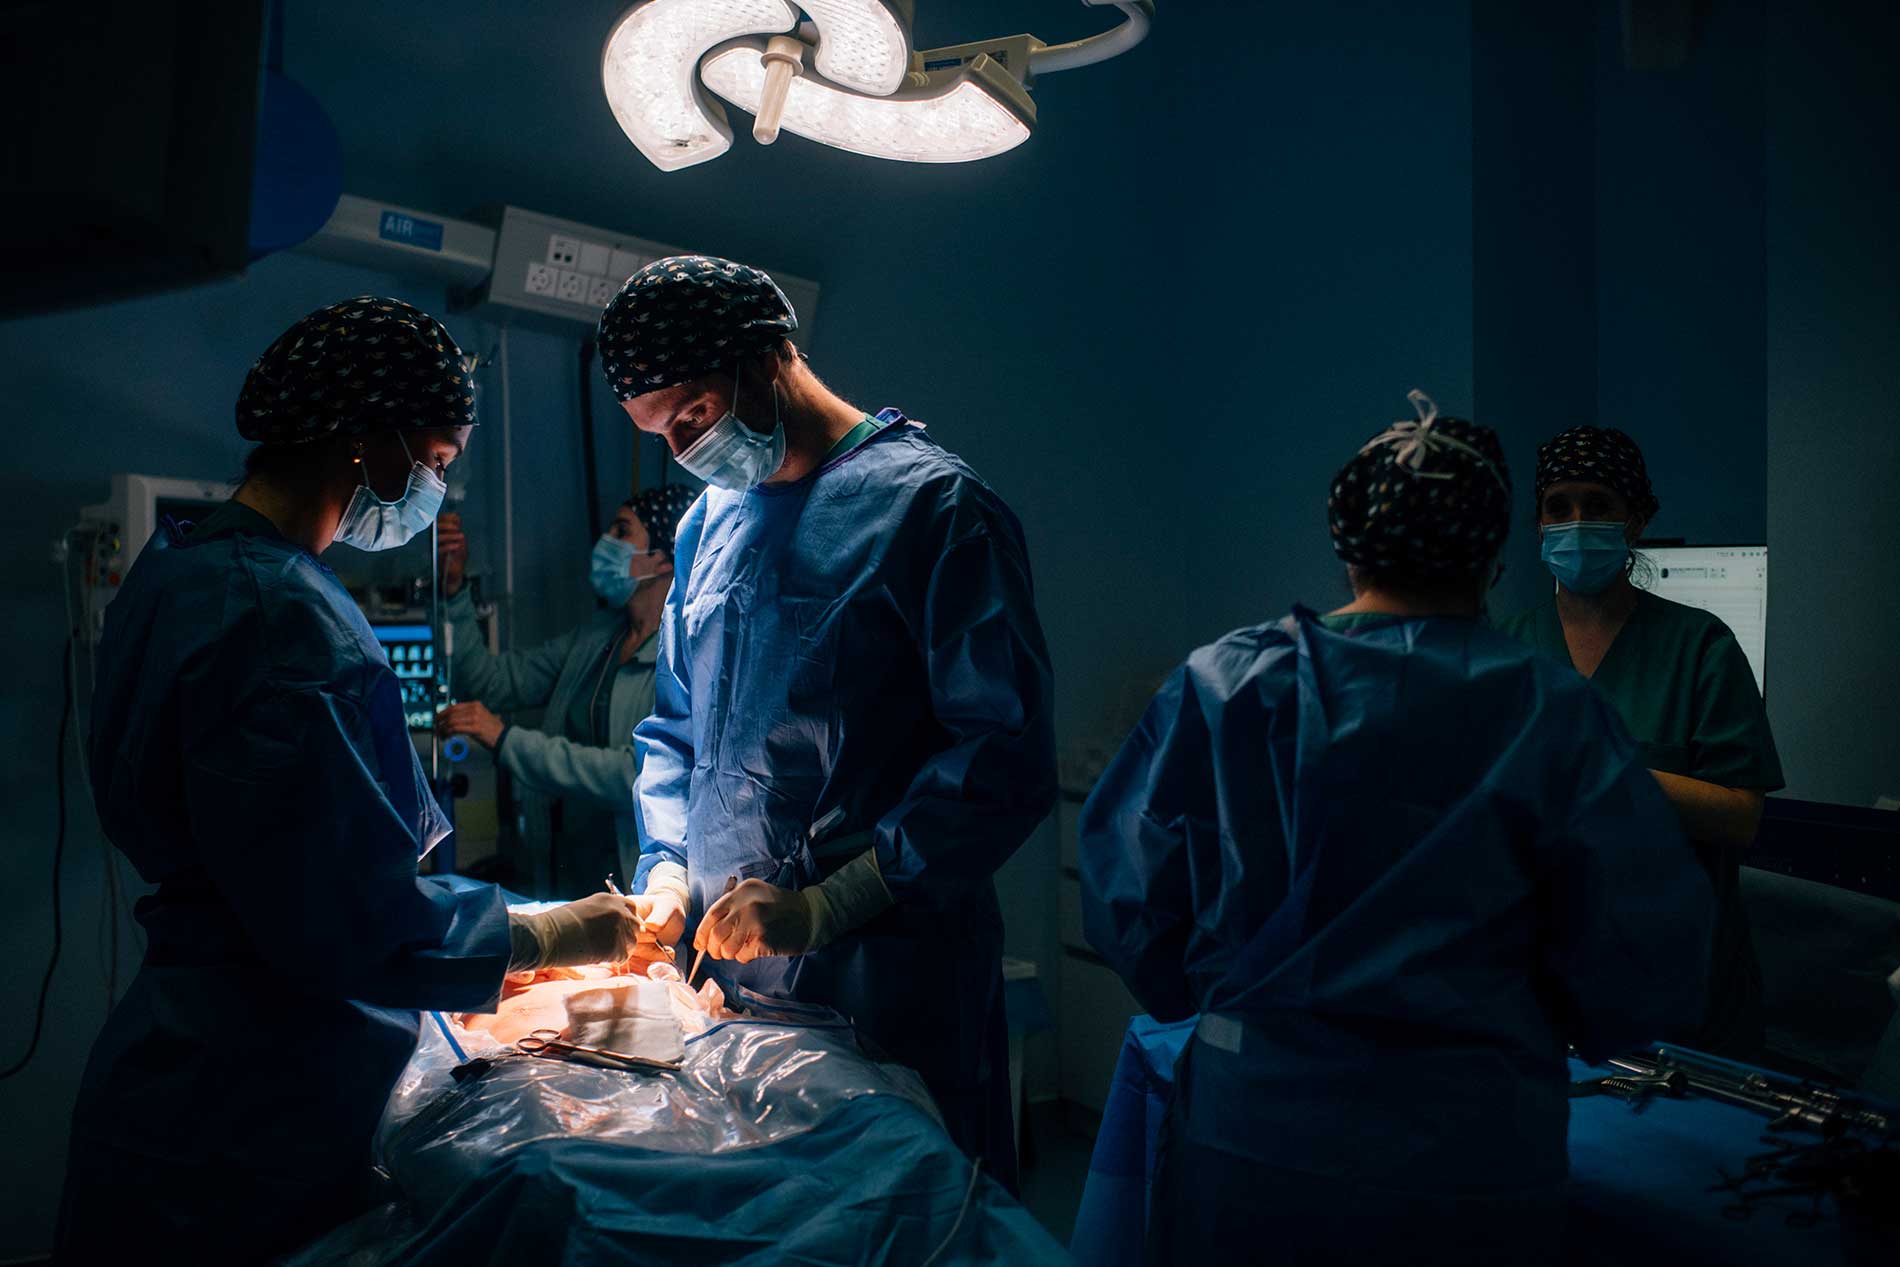
A complex multi-level laparoscopic surgery was performed:
- Laparoscopic myomectomy: Enucleation of 6 to 7 large fibroids in the anterior and fundal walls, whilst preserving the integrity of the endometrial mucosa (without opening the uterine cavity).
- Correction of Cervical Incompetence: Removal of the previous cerclage band and placement of a new laparoscopic abdominal cerclage at the upper isthmocervical junction, above the uterosacral ligaments.
Phase 3: Hysteroscopic Optimisation and Endometrial Regenerative Therapy (July 2025)
- Surgical Resectoscopic Hysteroscopy: Treatment of intra-cavitary scar tissue and release of microadhesions formed following myometrial surgery.
- Regenerative Treatment: Intrauterine application of Revitalize (PRP) to restore the endometrial stroma damaged by myometrial pathology.
Phase 4: Endometrial Preparation and Embryo Transfer (October 2025)
- Transfer: On 22/10/2025, the single euploid embryo was devitrified and transferred under high-resolution ultrasound guidance, being placed atraumatically in the upper anterior wall of the endometrium.
5. Outcome and Obstetric Course
Pregnancy Test (β𝛽-hCG): Positive with adequate doubling of plasma levels.
- High-Risk Pregnancy: Referral for management to a Maternal-Fetal Medicine unit with fortnightly ultrasound scans, monitoring of cervical length and relative bed rest.
- Outcome of the Pregnancy: In June 2026, upon reaching 34 weeks’ gestation and after confirming foetal lung maturity, a scheduled elective caesarean section was performed, resulting in the birth of a healthy baby girl with no immediate neonatal complications.
6. Conclusions and Clinical Relevance
This case represents one of the most complex scenarios in reproductive and maternal medicine:
- Efficacy of High Abdominal Cerclage in Severe Cervical Incompetence: Laparoscopic correction and repositioning of the cerclage at the level of the uterine isthmus is the technique of choice when previous vaginal or abdominal cerclages have failed.
- Conservative Uterine Reconstructive Surgery: It is possible to perform multiple myomectomies on uteri severely deformed by adenomyosis and fibroids without compromising the endometrial cavity, thereby enabling subsequent full-term pregnancies.
- Optimisation with a Single Embryo: The combination of PGT-A + Structured Surgery + Endometrial Regenerative Medicine (PRP) enables success rates of 100 per cent per transfer to be achieved, even in cases where only a single euploid embryo is available.


